

Built by a practicing veterinarian

YOUR NOTES
ARE ONLY THE
BEGINNING.

9-second notes. Real-time translation. Working in minutes. We built this because nobody else got it right.

Get the app Download on the App Store Google Play
Live Translate
● Beta · Patent Pending

Vetinuity hears which language your client speaks, Spanish, Mandarin, Hindi, Polish, and more, and translates the exam live, both directions. No language picker, no setup.

9 SEC

Average. Note done.

Finish the exam, and the note is already written. Nine seconds, on average, from last word spoken to finished SOAP note.

WORKING IN
MINUTES

Built-in templates from day one, or paste in your own. No template builder. No drag-and-drop wizard.

Built by Brian Toncray, DVM, a practicing emergency veterinarian in Phoenix.

/ 01 AND IT DOES ALL OF THIS TOO.

/ 01

CRI calculators + dilutions

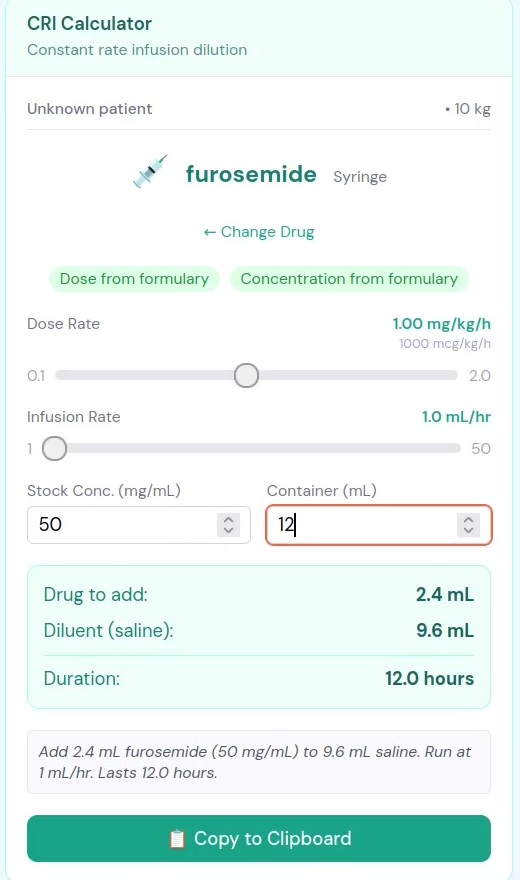
Furosemide CRI at 1 mg/kg/h diluted into a 12 mL syringe running at 1 mL/h. Math done.

/ 02

Capture by camera

Photograph a label to add the patient, labwork to flag the abnormals, or another vet's records for a summary, straight into the chart.

/ 03

Discharge, plain language

Client-ready discharge summaries generated from the medical note in seconds.

/ 04

Templates without a builder

Paste your existing template. Save. Done. No drag-and-drop wizard.

/ 05

Notes that sound like you

Professional clinical language, not robotic filler. Notes that read the way you'd write them.

/ 06

Works on any device

Phone in the exam room, desktop at the workstation. Everything syncs.

/ 07

Multipet exams

Add the patients into the exam and record like normal. As you dictate your findings for each pet, Vetinuity builds records for each patient.

/ 08

Vetinuity Rounds

Record rounds at the start of a shift and Vetinuity creates the patients, enters the signalment, and builds the board. SOAPs, labwork photos, and updates keep it current for the next doctor.

/ 02 DOSE MATH.
SPECIES AWARE.

Enter the patient, the drug, the route. Get the dose, the dilution, and the rate. Worked end to end. No scratch paper.

Furosemide CRI calculator showing worked dilution: 2.4 mL drug, 9.6 mL saline, run at 1 mL/hr for 12 hours.

/ 03 JUST TALK.
VETINUITY DOES THE REST.

You speak during the exam. Vetinuity captures the audio, transcribes it, builds the SOAP note, and surfaces the active problems, differentials, recommended diagnostics, and treatment options. Every claim is grounded in the literature.

● CLINICAL INSIGHT Feline · Chronic kidney disease, Stage 2 · Apr 14, 2026 Scroll ↓
Problems 3

HIGH Chronic kidney disease: IRIS Stage 2

Creatinine 2.1 mg/dL and SDMA 18 µg/dL confirmed on two samples taken two weeks apart. Staging CKD using the IRIS system is essential. It directs management decisions and establishes a prognostic baseline; early-stage identification is associated with markedly longer survival times.[1] Substage by UPC ratio and systolic blood pressure before finalizing the treatment plan.

MODERATE GI signs with risk of negative energy balance

Patient is hyporexic; 0.4 kg weight loss since last visit. Uremic nausea is the likely driver. Aggressive early nutritional support alongside IV fluids and antiemetic coverage substantially improves recovery trajectory when GI compromise accompanies systemic illness.[2]

MODERATE Suspected concurrent hyperthyroidism

Total T4 pending. Hyperthyroidism elevates GFR and can mask a worse stage of underlying renal disease; treating hyperthyroidism may unmask true CKD severity. Recheck creatinine and SDMA 4–6 weeks after initiating antithyroid therapy.

Recommended Diagnostics 5

HIGH Urine protein:creatinine ratio (UPC)

Required for IRIS substaging. Persistent proteinuria (UPC > 0.4) carries independent negative prognostic weight and is an indication for renoprotective therapy regardless of azotemia stage.

HIGH Systolic blood pressure

Hypertension accelerates glomerular injury in CKD. Target < 140 mmHg. If white-coat effect is suspected, measure on a separate low-stress visit before initiating amlodipine.

HIGH Total T4 (± free T4 by equilibrium dialysis)

Rule out occult hyperthyroidism before staging is considered stable. A normal total T4 in a cat with comorbidities can be spuriously suppressed; free T4 by equilibrium dialysis is more sensitive if index of suspicion is high.

SUGGESTED Abdominal ultrasound

Assess renal architecture: cortical echogenicity and corticomedullary distinction. Small, irregular kidneys with increased echogenicity support chronic fibrosis rather than an acute injury pattern.

SUGGESTED Repeat chemistry in 4–6 weeks

Per IRIS criteria, two creatinine and SDMA measurements separated by at least two weeks are required to confirm staging. Single-point values can be influenced by hydration status and lean muscle mass.

Treatment Considerations 4

Phosphorus restriction

Transition to a renal diet; target serum phosphorus 2.5–4.5 mg/dL for IRIS Stage 2. Add an intestinal phosphate binder if dietary restriction alone fails to reach target after 4–8 weeks of confirmed compliance.

Methimazole if hyperthyroidism confirmed

Initiate at 1.25–2.5 mg per cat orally twice daily (q12h). Twice-daily dosing achieves euthyroidism in significantly more cats at 2 weeks and produces fewer serious adverse effects than equivalent once-daily dosing.[3] Recheck T4 and renal values in 2–3 weeks; adjust dose in 1.25 mg increments until euthyroid.

Amlodipine if SBP > 160 mmHg on two readings

Start amlodipine 0.625 mg/cat PO q24h. Recheck blood pressure in 7–14 days. Titrate to 1.25 mg if target not reached. Do not use benazepril as monotherapy for hypertension in CKD. Combination therapy with amlodipine is preferred when proteinuria is present.

Recheck schedule: IRIS Stage 2

Creatinine, SDMA, UPC, and blood pressure every 3–6 months at baseline. Advance to every 1–3 months if UPC > 0.4 or SBP > 159 mmHg at any visit.

/ 04 REAL EVIDENCE. REAL SOURCES. EVERY TIME.

10,000+
Peer-reviewed veterinary journal articles indexed into the clinical corpus.
EVERY.
Recommendation cited. Author, journal, year on demand. No black box.
AUTO.
No prompting needed. Insights surface while you work the case.

/ 05 FINISH YOUR CHARTS BEFORE YOU LEAVE.

Open Vetinuity →
● UPDATES